Case #1210
Direct-to-Implant Reconstruction
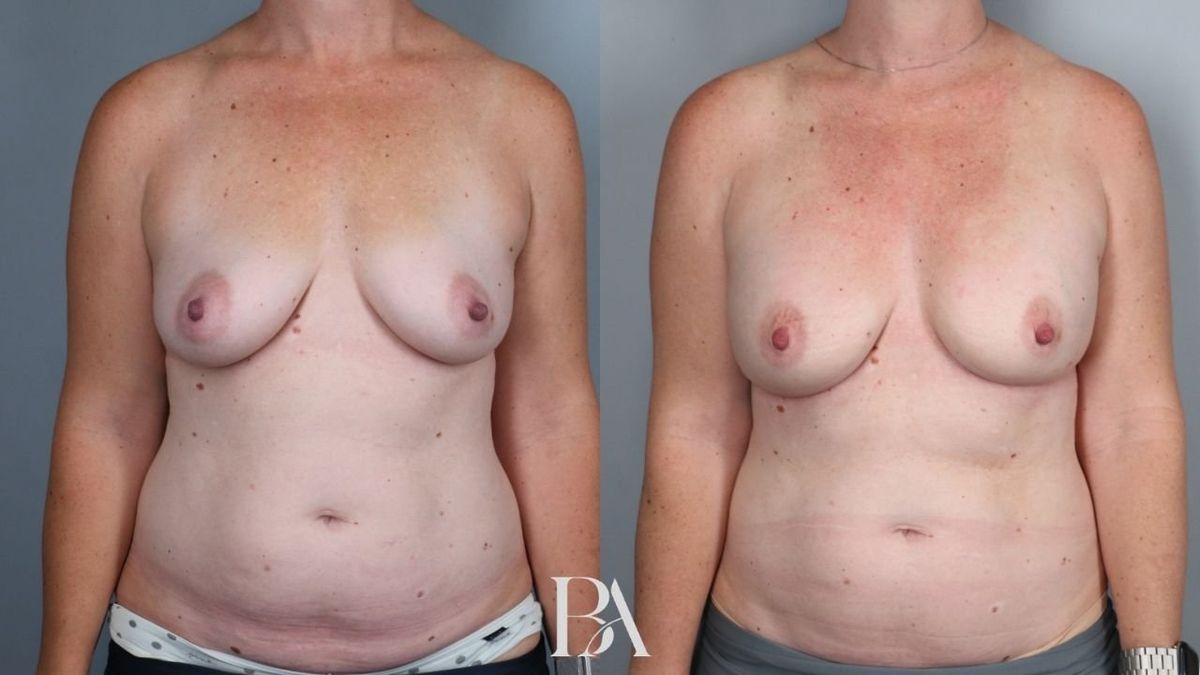
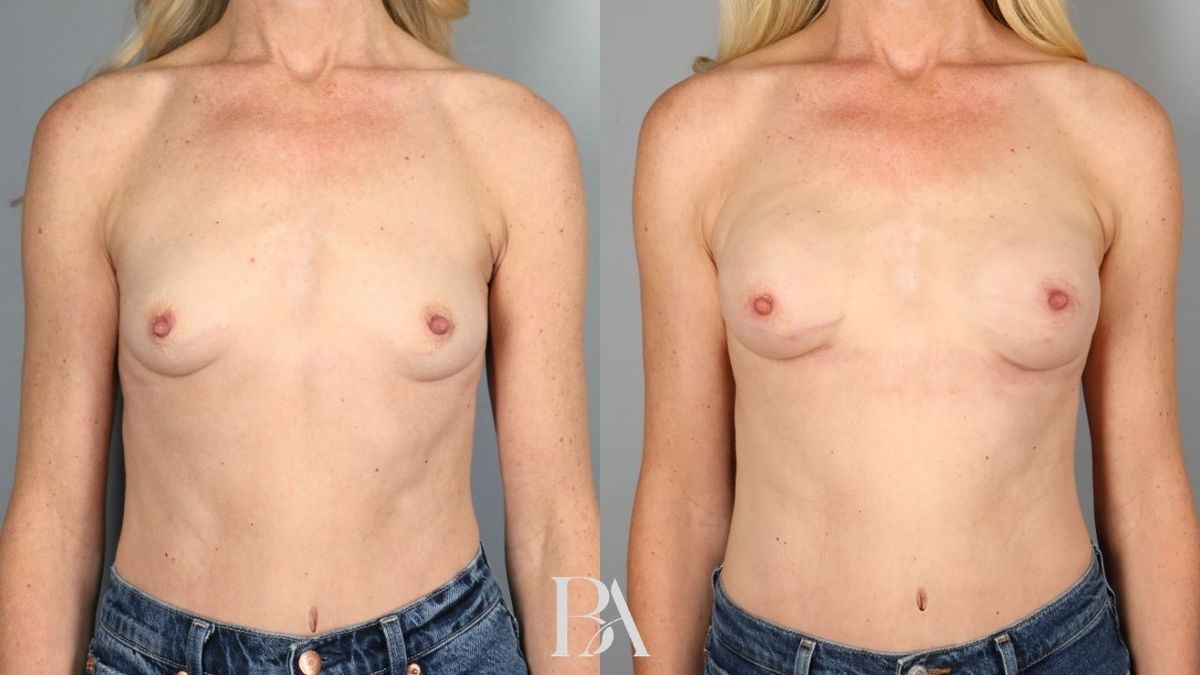
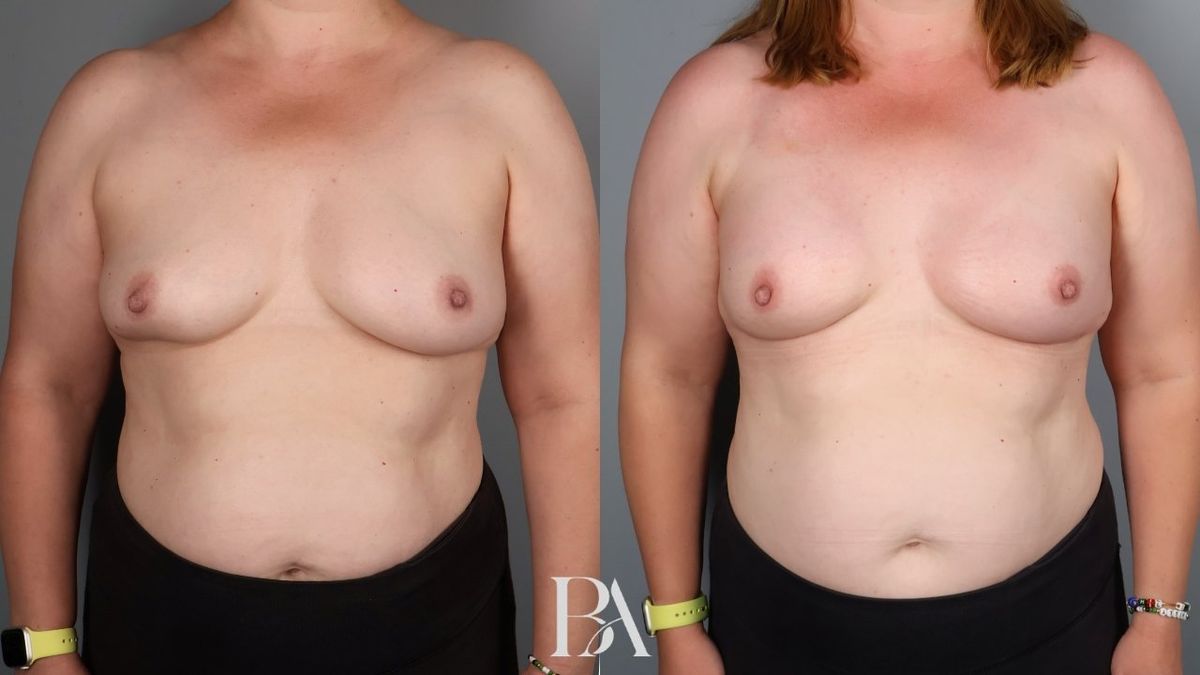
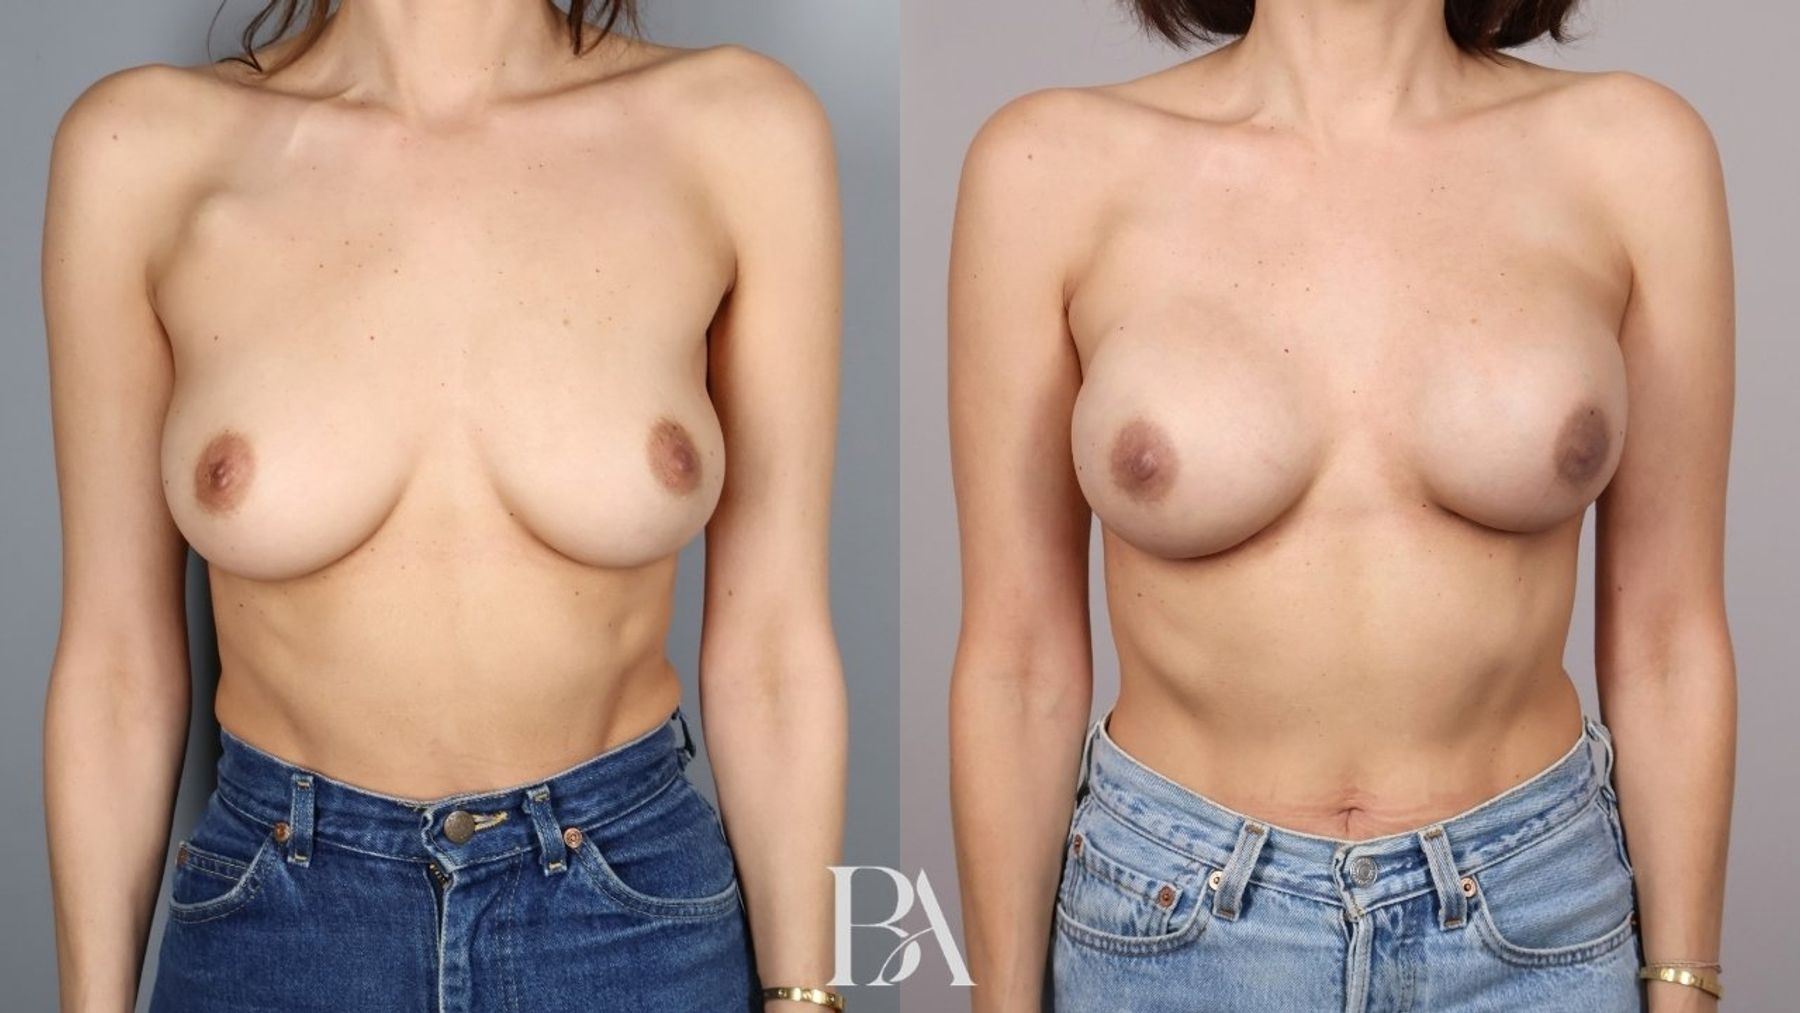
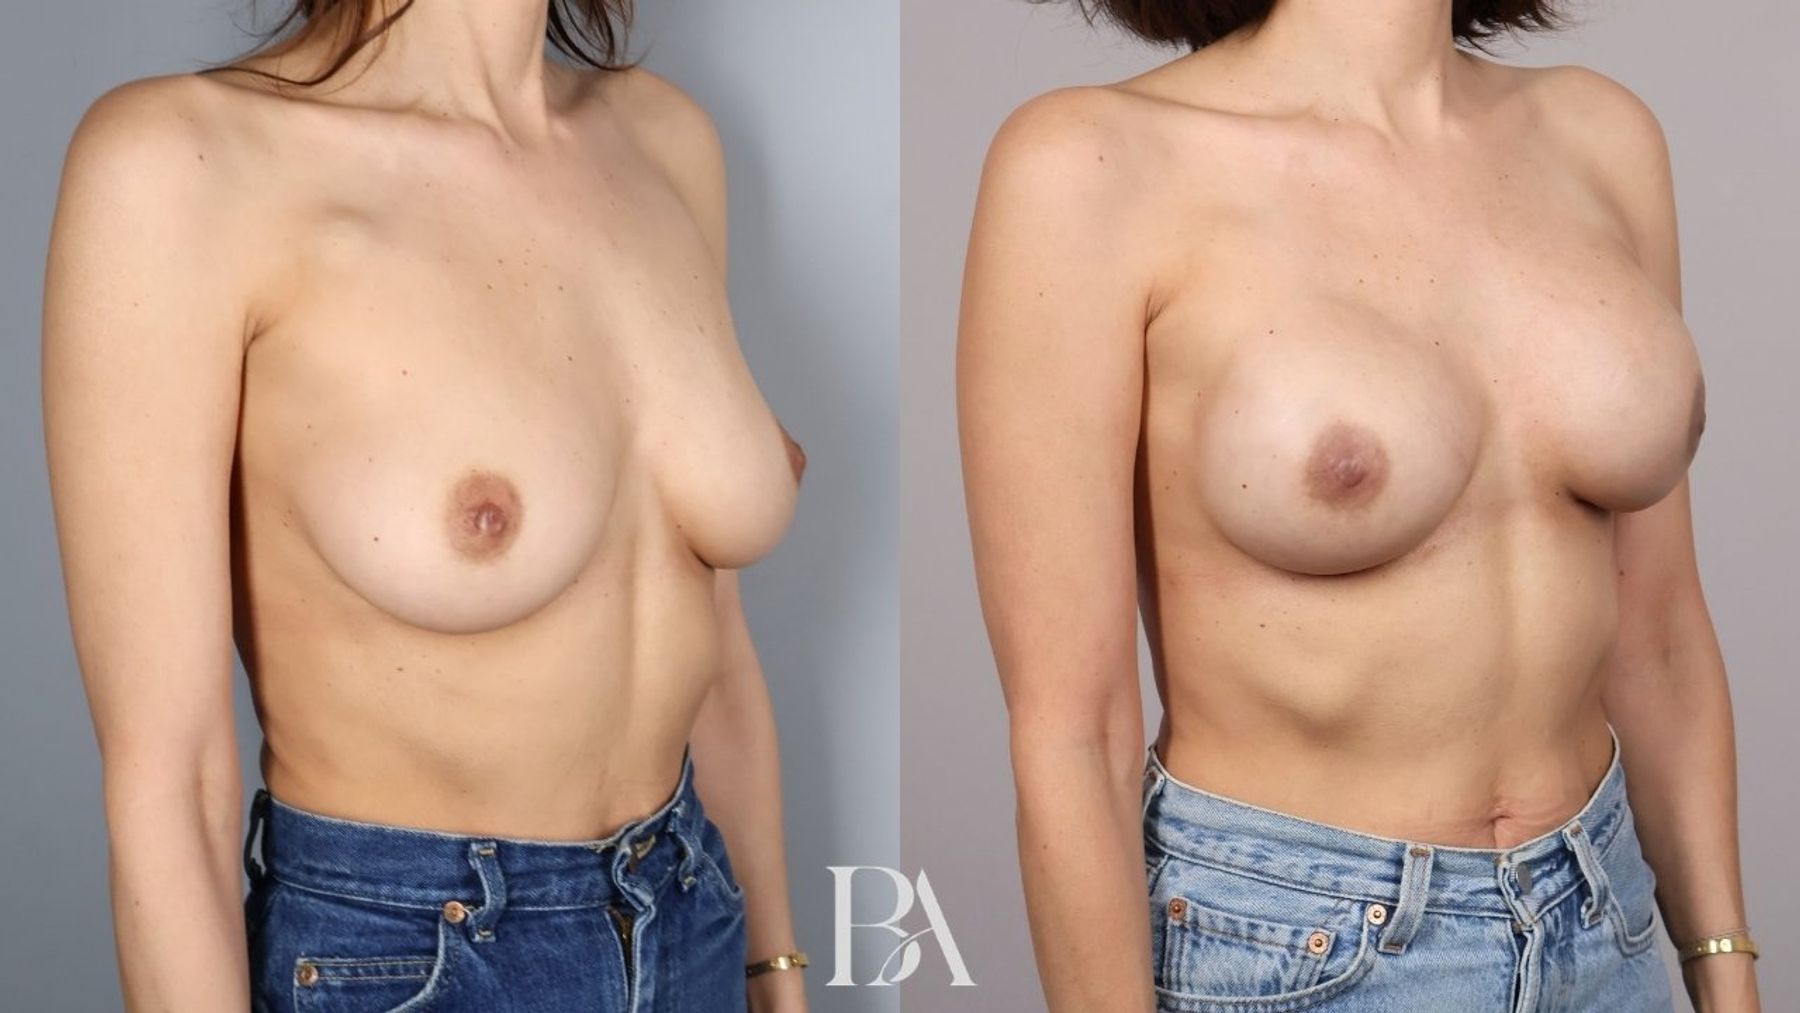
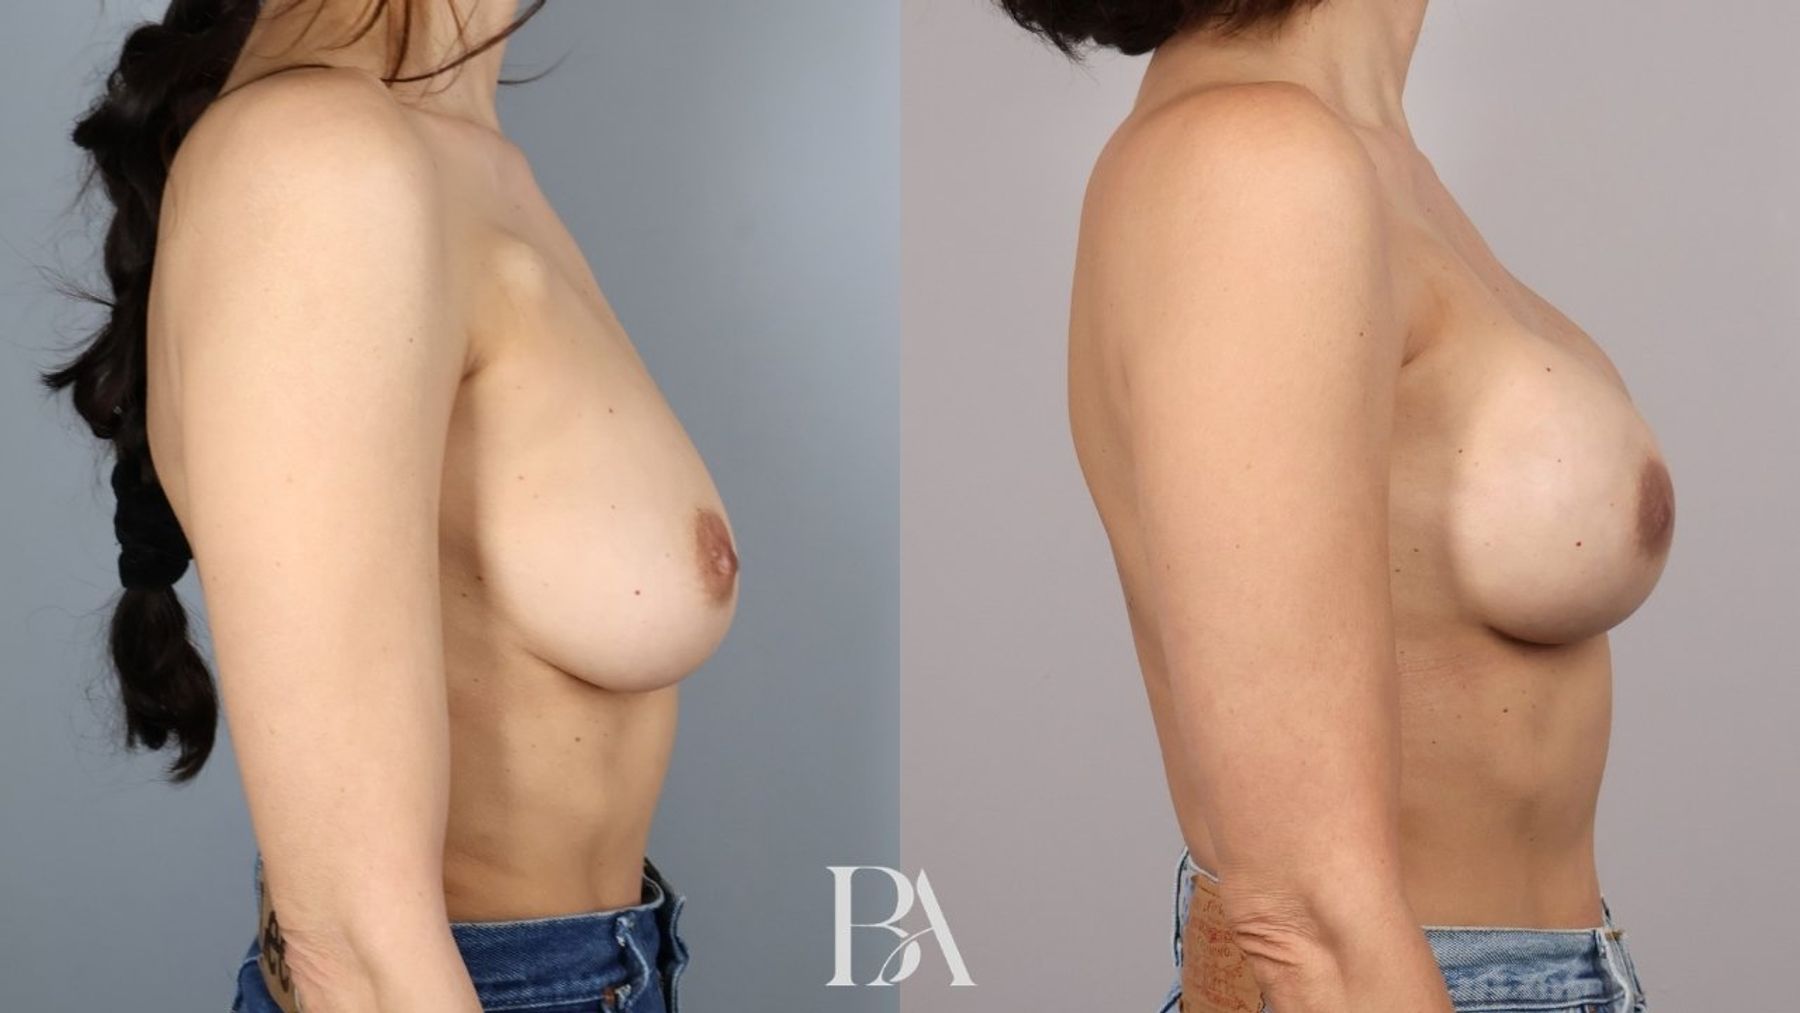
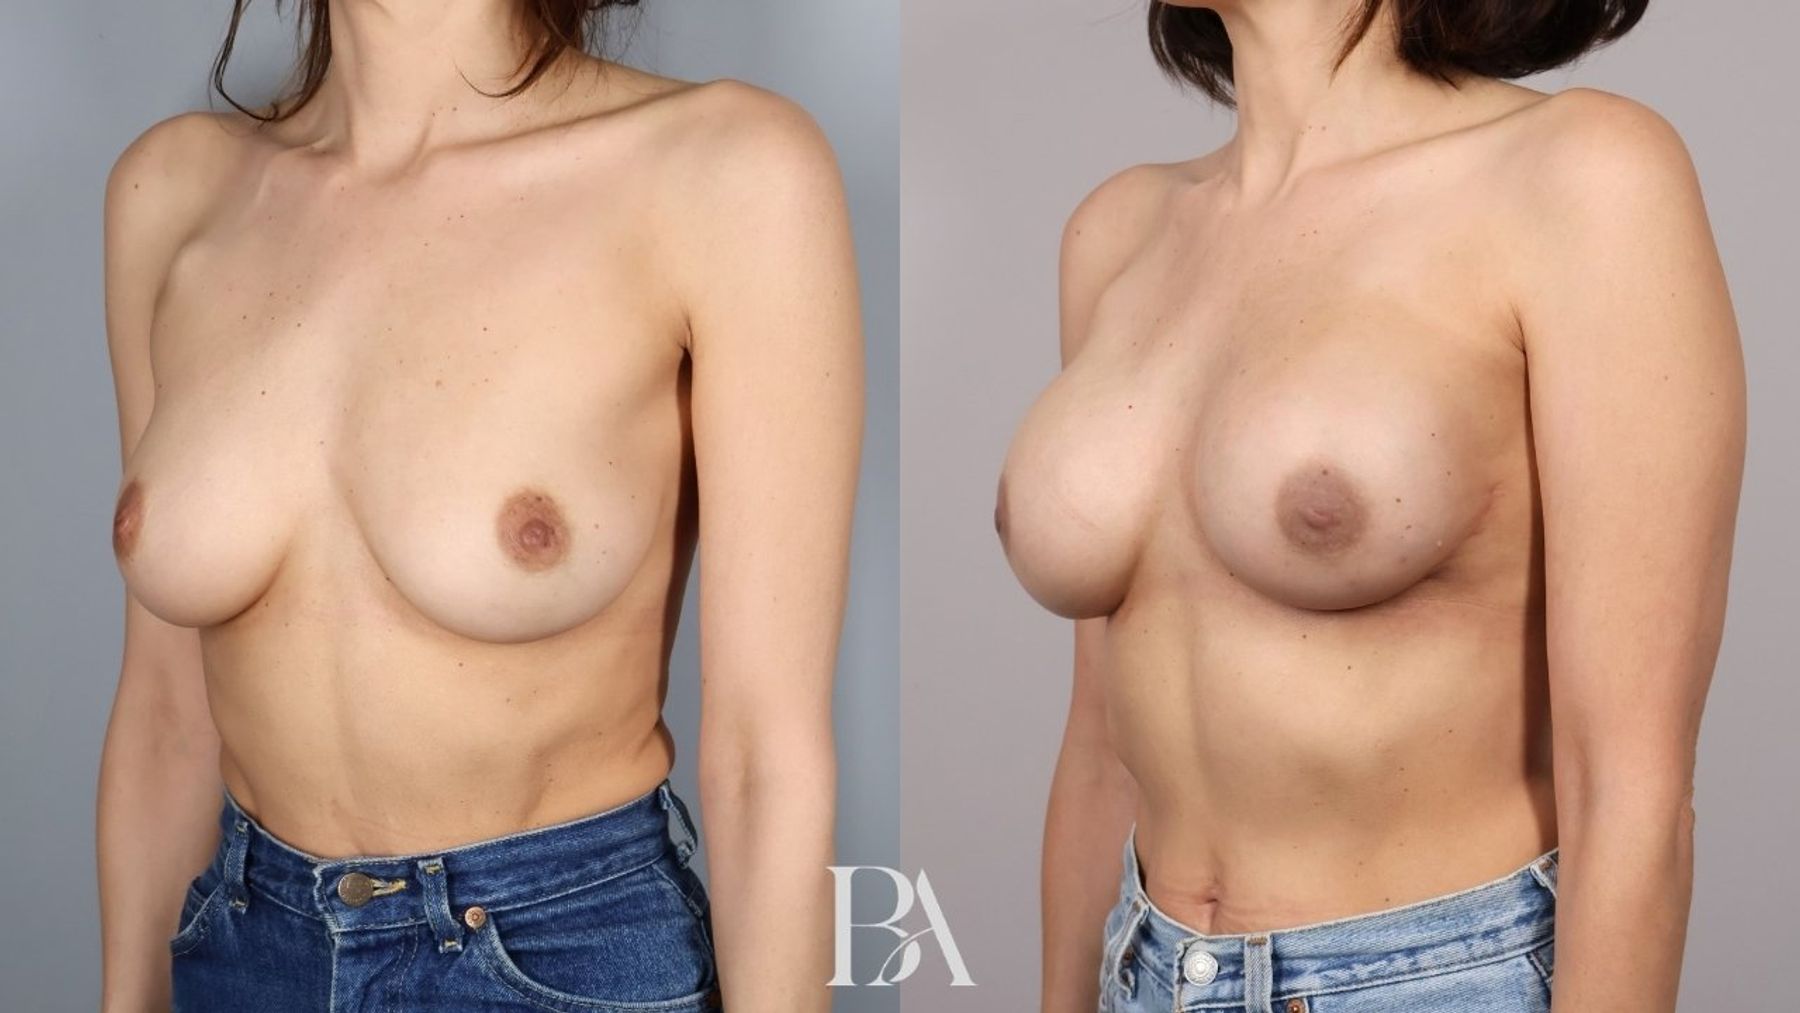
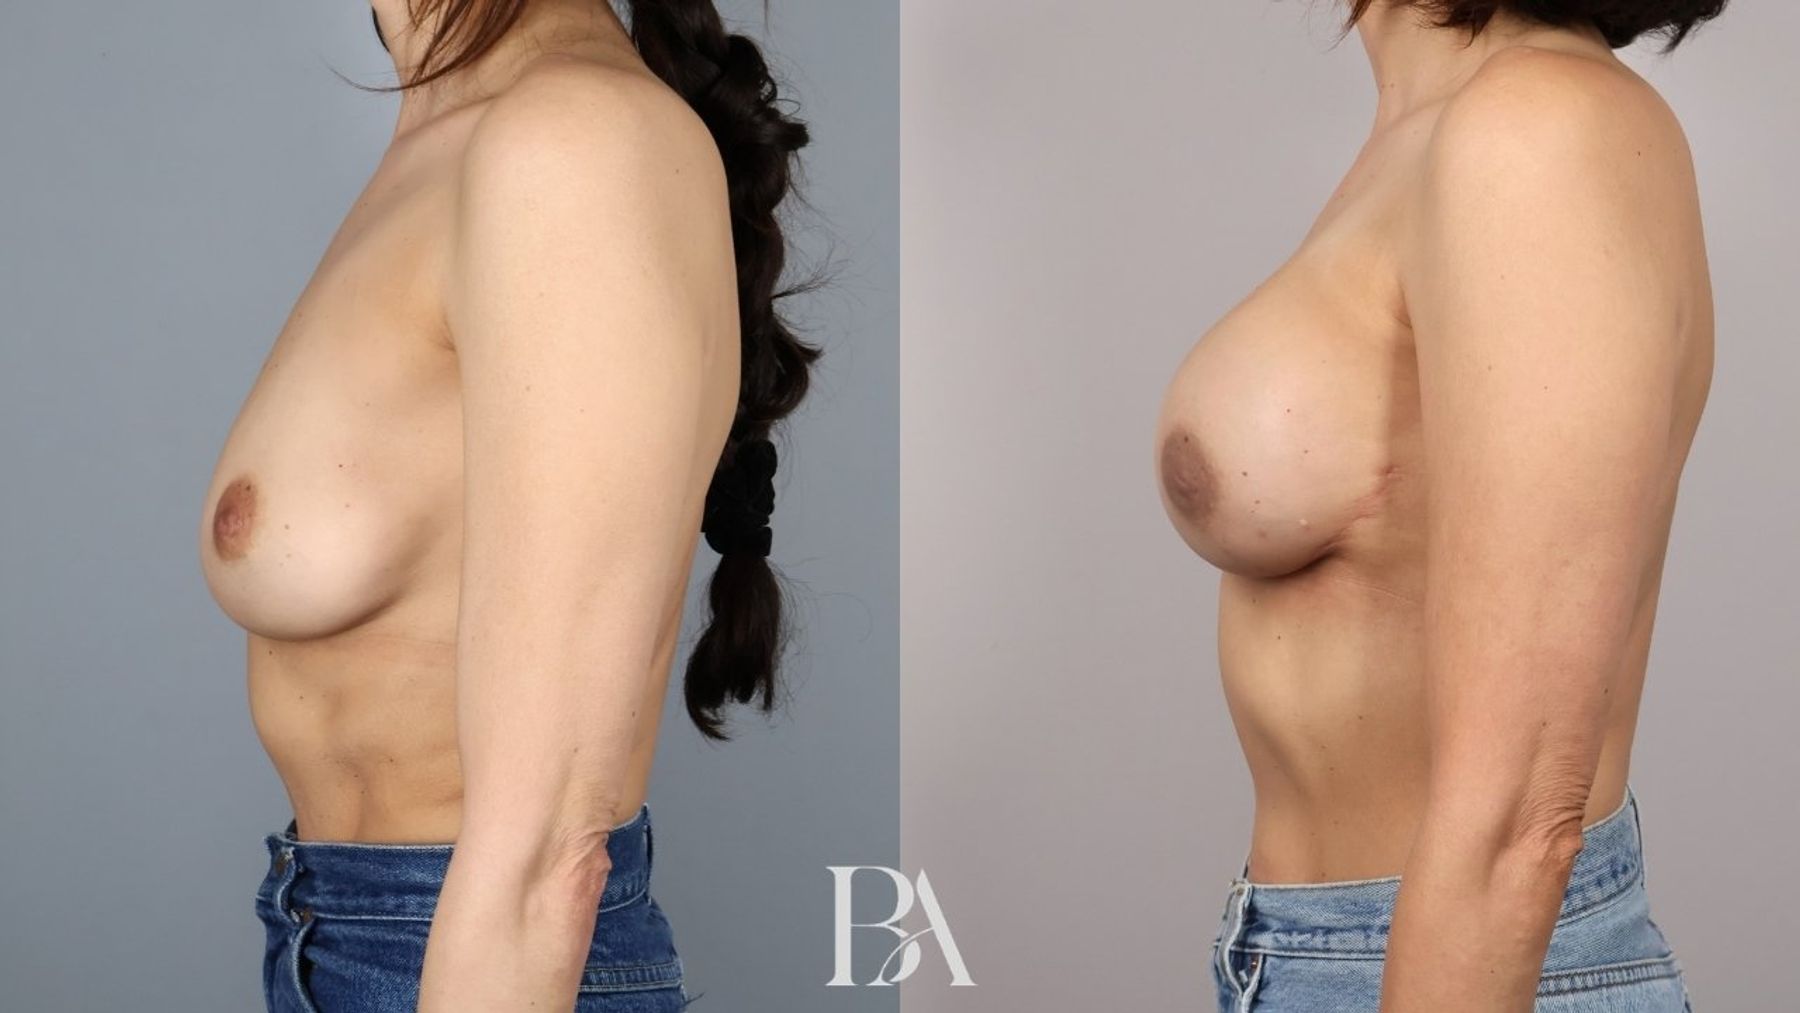
A woman in her 40s with left breast cancer had a bilateral nipple-sparing mastectomy with direct-to-implant reconstruction, followed by radiation to the left breast. Shown 9 months after surgery.
A woman in her 40s with left breast cancer chose a bilateral nipple-sparing mastectomy. Dr. Azadgoli performed direct-to-implant reconstruction at the same operation. The patient then completed radiation to her left breast. Her result is shown 9 months after surgery and 4 months after radiation ended.
Why this approach
The decisions that shaped this surgical plan.
- Reconstruction planned around the oncologic mastectomy — surgical timing, tissue preservation, and incision pattern were chosen to support both safe cancer clearance and long-term aesthetic outcome.
- Both sides treated in the same session — symmetric planning, identical tissue handling, and matched final contour are easier to achieve in one operative window than in two.
- Nipple-sparing mastectomy chosen to preserve as much native tissue as oncologic safety allowed — better reconstructive canvas, less scarring.
Pre-op preparation
What to do before surgery. Specific to this case.
- Aspirin, ibuprofen, vitamin E, and fish oil discontinued 14 days pre-op to reduce bruising risk. Acetaminophen is allowed.
- Full nicotine cessation 6 weeks pre- and post-op. This includes vapes and nicotine replacement products; the constriction effect is the same.
- No overhead clothing for 3 weeks. Stock front-zip tops, supportive sports bras (post-clearance), and the drain pouches we provide.
- A driver is required the day of surgery and a responsible adult should stay with you the first 24 hours.
- Surgical date confirmed against oncology pathway. Imaging and pathology results are reconciled by the team at the pre-op visit.
Recovery timeline
Milestones specific to this case. Individual recovery varies.
- Day 1–7
Drain care, low-lift movement, and rest through the first week. Nerve blocks (Exparel) cover the worst of the pain through day 3.
- Week 2
Drains typically come out toward the end of the week. Suture lines are inspected; lymphatic drainage begins once approved.
- Week 4
Most patients back to gym cardio at 50 percent intensity. Scar massage protocol begins. Driving restored if not already.
- Week 6
The "back to normal" week for most patients. Final compression schedule transitions to optional.
- Month 3
Coordinated oncology and surgical check-in. Reconstruction shape and feel begin to mature.
- Month 6
Mature result. Patients commonly schedule the final phase of staged reconstruction here.
Continued care
Recommended aftercare, skincare, and MedSpa services for Direct-to-Implant Reconstruction.
- Compression bra continuously for 6 weeks
- Drain care taught before discharge; removed when output is low (typically 1–2 weeks)
- Sleep elevated on your back for 2 weeks
- No lifting above 10 lb for the first 3 weeks
- Follow-up imaging coordinated with the oncology team
- Medical-grade silicone sheeting on the mastectomy incision
- SkinCeuticals C E Ferulic for scar healing
- SPF 50+ on incisions for 12 months
- Priority lymphatic drainage starting week 1
- LED light therapy weekly for the first 8 weeks
- Fractional laser for scar refinement after 3 months
- Aftercare
Bilateral HBOT protocol — 10–15 sessions over the first 6 weeks.
Bilateral procedures heal more reliably with sustained HBOT.
- Coordination
Follow-up imaging schedule coordinated with the oncology team.
Post-mastectomy patients stay on a long-term surveillance pathway.
- Aftercare
Lymphatic drainage prioritized at week 1 to limit post-axillary swelling.
Lymphatic disruption from axillary work makes early drainage more valuable.
- MedSpa
Aggressive skin treatments deferred until month 6 — reconstructed tissue softens on its own timeline first.
Reconstructed tissue softens more slowly than primary breast surgery.